PDE5 inhibitors and alpha blockers: how clinicians reduce the blood-pressure risk
Sildenafil or tadalafil can add to the blood-pressure effects of alpha blockers. Learn why stability, dose and symptoms matter before combining them.
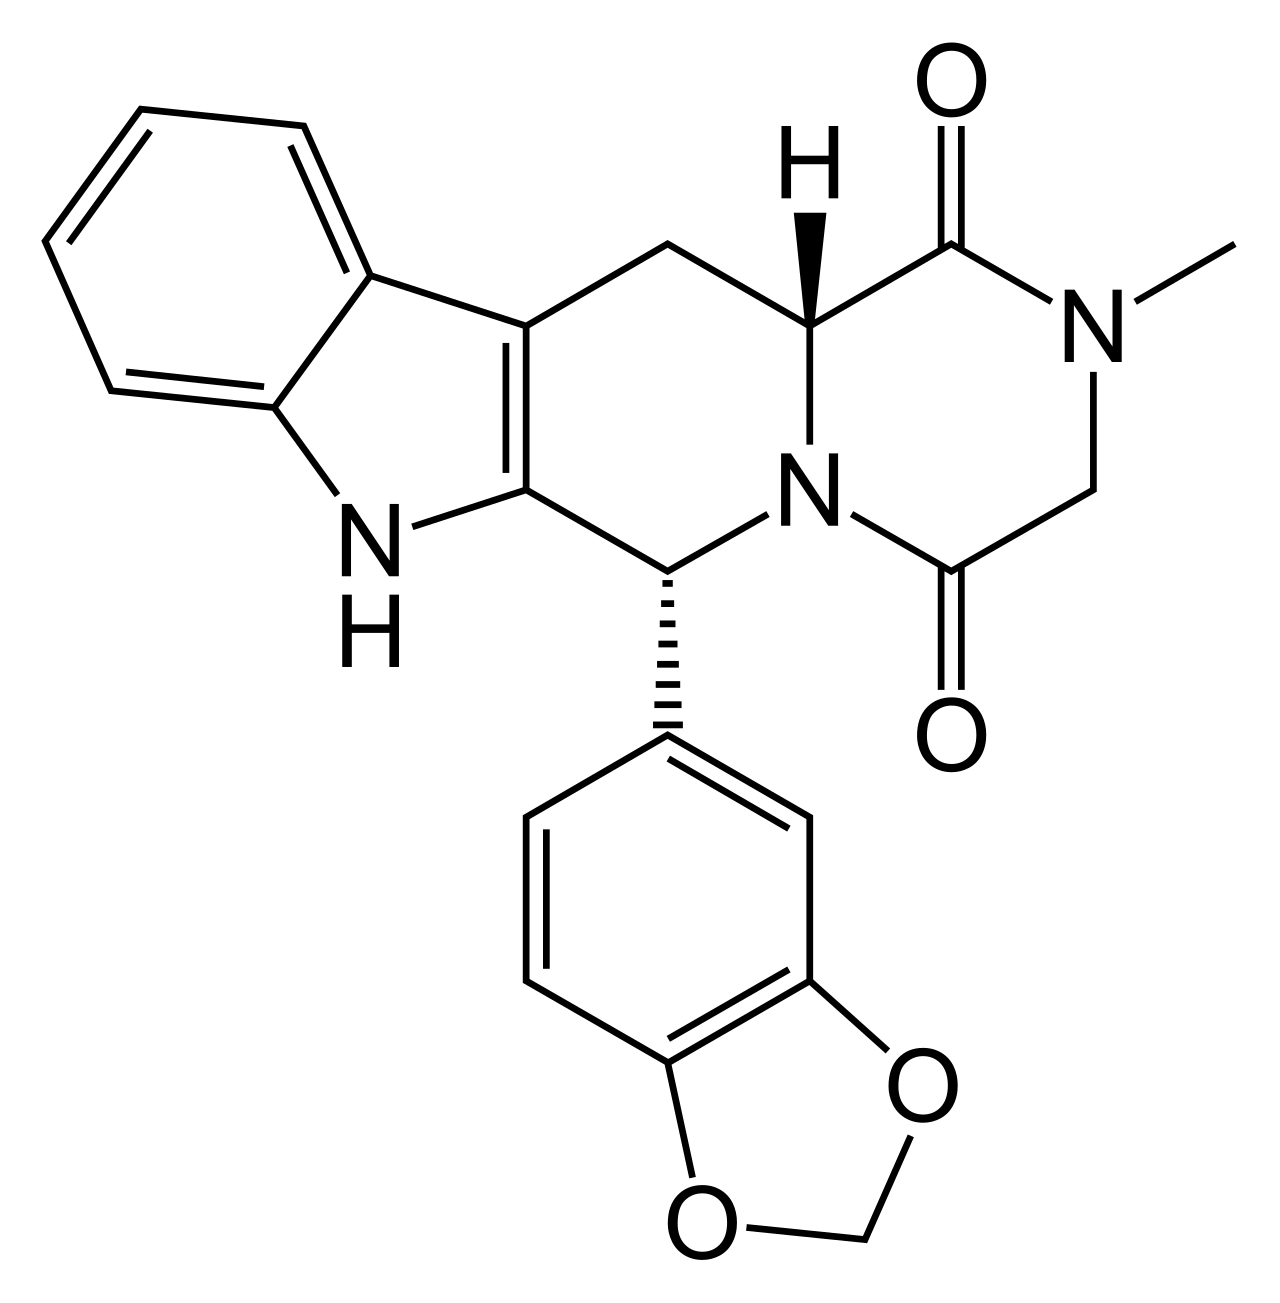
The combination is not automatically forbidden, but it needs a clinician-led plan. Stable alpha-blocker therapy, a low starting PDE5 dose and attention to dizziness or fainting can reduce avoidable risk.
Two useful medicines can pull pressure in the same direction
Alpha blockers such as tamsulosin, doxazosin and terazosin relax smooth muscle and are commonly used for urinary symptoms from an enlarged prostate; some also treat high blood pressure. PDE5 inhibitors relax vascular smooth muscle through a different target. When the effects add together, standing blood pressure can fall enough to cause lightheadedness, weakness or fainting.
This is a different problem from the absolute nitrate contraindication, but it still deserves more than a quick interaction check. The effect depends on the specific alpha blocker, dose, timing and the person’s usual pressure. Hidden PDE5 analogs make that review harder because an undeclared drug can add vascular effects that neither the patient nor prescriber expected.
What sildenafil labeling actually recommends
Current sildenafil labeling says patients should be stable on alpha-blocker therapy before sildenafil begins, and sildenafil should start at the lowest dose. Stability means the alpha blocker is already tolerated without problematic low pressure; it does not mean the interaction disappears. Dehydration, alcohol, other pressure-lowering medicines or a recent dose change can make symptoms more likely.
Sildenafil’s meal timing may change onset, yet a slower start does not make an unsafe combination safe. The prescriber needs the exact alpha-blocker name because selective and nonselective drugs do not have identical hemodynamic profiles. A label-based plan is more reliable than spacing advice copied from another person’s prescription.
Tadalafil evidence needs context
A 12-week randomized trial enrolled 318 men already receiving stable alpha blockers for prostate symptoms. Dizziness and positive orthostatic tests were similar with tadalafil 5 mg and placebo overall, although the authors noted a trend toward more hemodynamic effects with nonuroselective agents, especially doxazosin. That supports careful use in selected patients, not unrestricted mixing.
Daily tadalafil keeps drug exposure in the body, while as-needed use creates a different timing pattern. An antioxidant evidence review offers a useful contrast: pooled supplement results do not answer a prescription interaction question. Neither schedule replaces a review of blood pressure, prostate therapy and other medicines. Do not retime an alpha blocker without its prescriber.
The alpha blocker matters. Tamsulosin is relatively selective for prostate receptors, while doxazosin and terazosin have broader blood-pressure effects. That does not make any pairing automatically safe; it explains why a prescriber asks for the exact name rather than accepting “a prostate pill” as enough information.
Know the warning symptoms
Sit or lie down if you become suddenly lightheaded. Seek urgent care for fainting, chest pain, severe weakness, confusion or an erection lasting four hours. Repeated mild dizziness also deserves a call because it may signal that the doses, timing or broader medication list need attention.
Yohimbe and yohimbine can affect heart rate and pressure too, which is one reason a supplement belongs in the medication review. The same goes for multi-ingredient blends: a formula trial does not establish the safety of every combination with prescription vasodilators.
Bring a precise list to the ED visit
PureBlue currently offers an online ED assessment for sildenafil and tadalafil, while its other men’s-health categories are marked coming soon. An online questionnaire can be convenient, but it only helps when the medication list is complete and a clinician determines suitability. Include the alpha blocker, dose, start date, symptoms and home pressure readings if you have them.
The useful takeaway is not “never” or “always.” It is: stabilize one therapy, start the other cautiously when approved, and respond to symptoms. That turns a vague interaction alert into a concrete plan tailored to the alpha blocker and your cardiovascular risks.
A home blood-pressure log can support the discussion, especially after a dose change, but symptoms still count. Record seated and standing readings, timing and dizziness rather than chasing one number. Fainting, chest pain, new weakness or a fall needs prompt assessment, not another experiment with dose spacing.
Bring every prescription bottle or a current pharmacy list to the visit. Brand names can obscure duplicate ingredients, while an old alpha blocker left on the chart may lead to the wrong conclusion about present risk.